Newborn breastfeeding mechanics rely on a deep latch, rhythmic tongue movement, breast compression, and coordinated suck-swallow-breathe patterns.
Newborn breastfeeding mechanics can seem mysterious at first. A baby must use the lips, tongue, jaw, cheeks, and breathing muscles as one small team. At the same time, the breast responds to touch and sucking by releasing milk. This guide explains each step in plain language, with research-based tips to make feeding more comfortable and effective.
What are newborn breastfeeding mechanics?
Newborn breastfeeding mechanics describe how a baby attaches to the breast, removes milk, swallows, and breathes during a feed. The process is more than simple sucking. It is a careful dance between the baby’s mouth and the parent’s breast.
A newborn uses several actions at once:
• The lips create a seal around the breast.
• The tongue cups the breast and moves milk toward the throat.
• The jaw moves in a slow, deep rhythm.
• The cheeks help keep suction steady.
• The soft palate and throat guide milk safely.
• The baby pauses to breathe between swallows.
Good newborn breastfeeding mechanics should feel like gentle pulling, not sharp pinching. You may notice a steady suck and swallow pattern once milk begins to flow.

How a newborn latch works
A latch is the way a baby takes the breast into the mouth. A deep latch allows the nipple to reach far back into the baby’s mouth. The baby should take in a good amount of the areola, especially from the lower part of the breast.
The nipple itself is not meant to carry all the pressure. Much of the milk removal comes from the tongue and jaw pressing the breast tissue behind the nipple. This is why a shallow latch can hurt and may remove less milk.
A helpful latch sequence looks like this:
-
Hold the baby close, with the chest facing your chest.
-
Line the baby’s nose with the nipple.
-
Brush the nipple across the upper lip.
-
Wait for a wide-open mouth.
-
Bring the baby to the breast, chin first.
-
Aim the nipple toward the roof of the mouth.
-
Check that the chin touches the breast and the nose remains free.
The baby should not need to twist the neck or reach forward. Think of the breast as a soft sandwich. The baby needs room to take a large mouthful, not just the tip.
Common signs of a deep latch include:
• The mouth is wide open.
• The lips turn outward.
• The chin rests against the breast.
• More areola shows above the top lip than below the bottom lip.
• The tongue stays under the breast.
• Sucking feels strong but not painful.

The role of the tongue, jaw, lips, and cheeks
The tongue is the main working part of newborn breastfeeding mechanics. It extends over the lower gum and forms a broad channel under the breast. A wave-like movement then presses milk toward the back of the mouth.
The jaw adds gentle compression. It should move deeply and slowly, rather than making quick, shallow motions. The lips help seal the breast, while the cheeks help maintain stability.
A newborn does not usually “pump” milk by squeezing the nipple alone. Instead, the baby compresses the breast tissue with the tongue and jaw. This action supports milk removal and helps signal the body to make more milk.
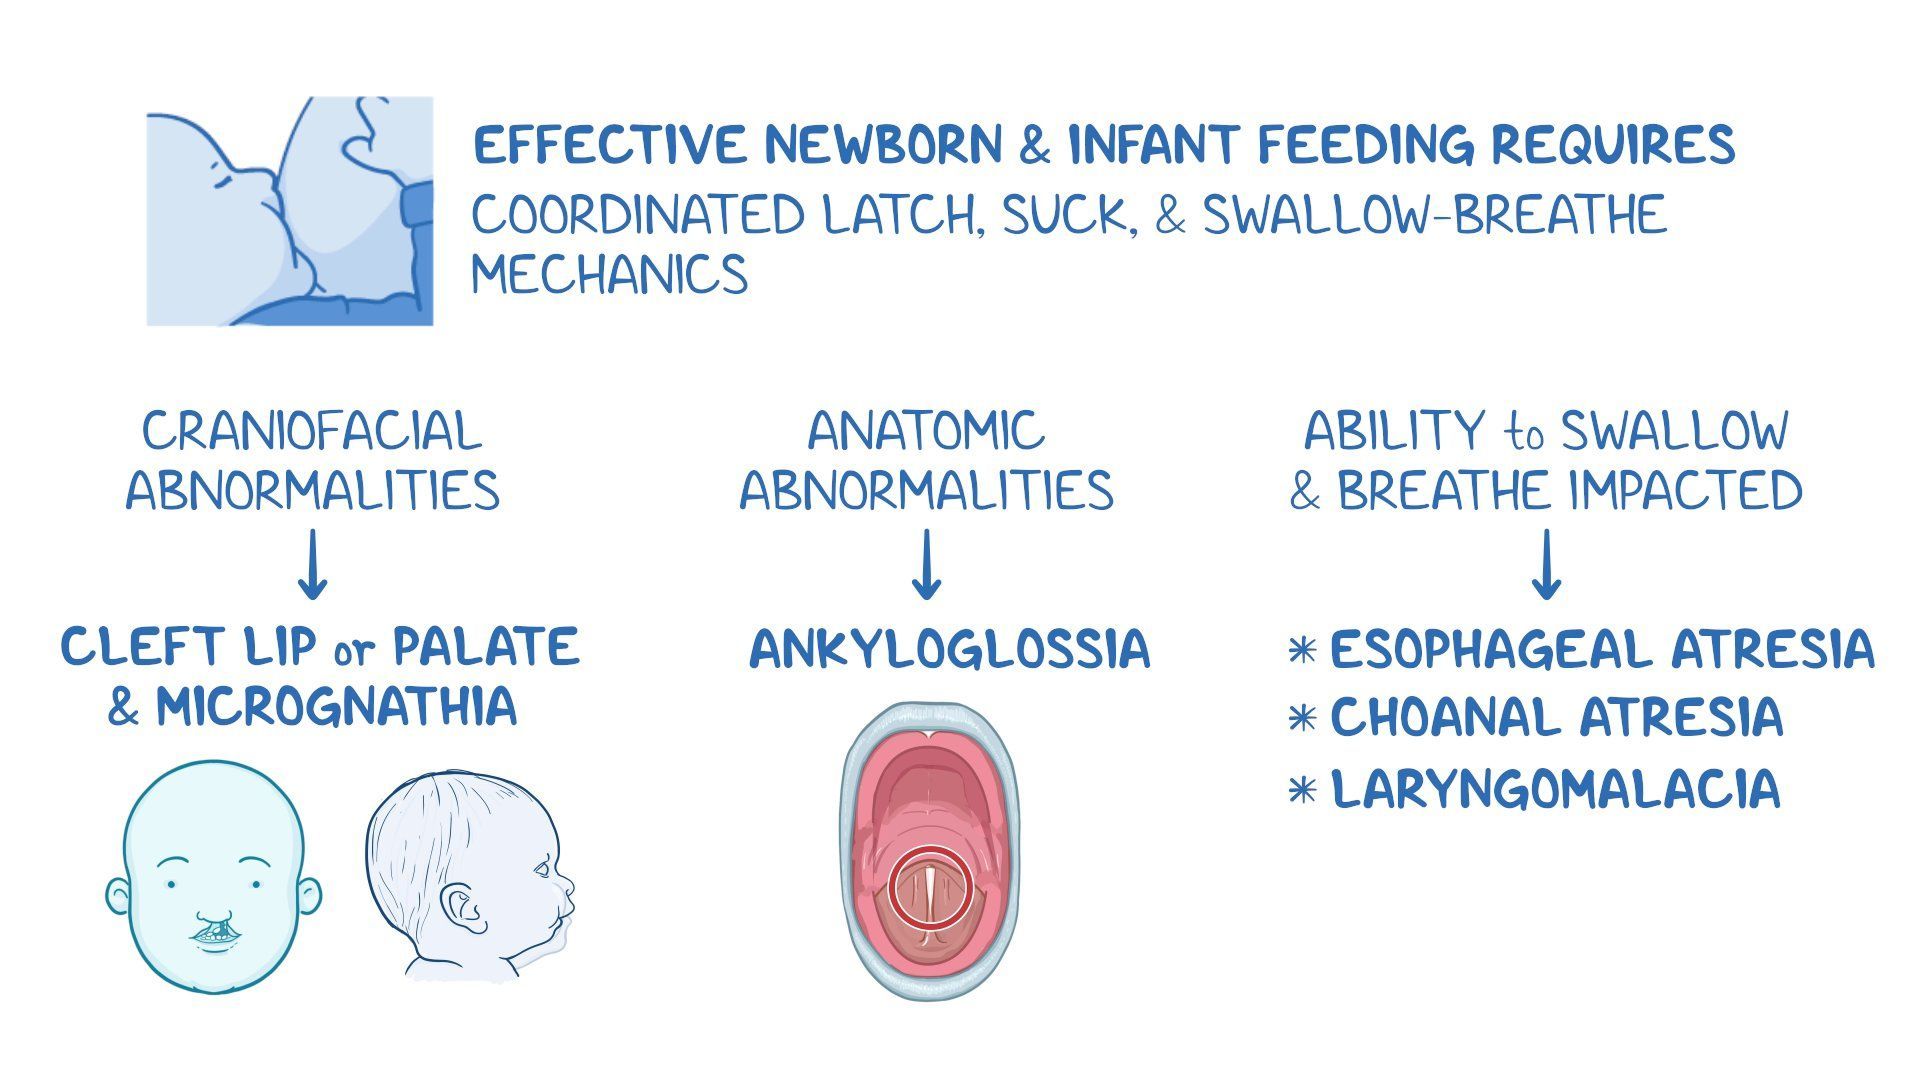
Some newborns have trouble with these movements. Prematurity, low muscle tone, oral restrictions, birth swelling, or sleepiness can affect feeding. A tongue-tie may also limit tongue movement, but appearance alone does not prove that it is causing a feeding problem. A trained health professional should assess milk transfer, comfort, and weight gain before treatment is considered.
One lesson often seen in feeding support is that parents may focus on the nipple position while missing the baby’s body position. A straight, well-supported body can improve the mouth’s work. Small changes, such as bringing the baby closer, can make a major difference.

How sucking, swallowing, and breathing work together
Newborn breastfeeding mechanics require the baby to coordinate three vital actions: sucking, swallowing, and breathing. This coordination is called suck-swallow-breathe rhythm.
At the start of a feed, a baby may use quick sucks. These light sucks help stimulate the nipple and trigger milk release. As milk begins to flow, the pattern often changes to slower sucks with visible or audible swallows.
A common rhythm may look like this:
• Several sucks occur close together.
• The baby pauses or changes jaw movement.
• A swallow may be heard as a soft “kuh” or quiet gulp.
• The baby takes a breath.
• The cycle repeats.
Some babies swallow silently, so sound is not the only sign. Look for a brief pause in jaw movement, a change in the cheek, or a relaxed hand and body.
Newborns may cough, gulp, or pull away when milk flows quickly. This does not always mean a serious problem. Try a more reclined position, allow the first strong flow to pass into a towel, or offer short pauses. Seek advice if the baby often chokes, turns blue, struggles to breathe, or cannot stay attached.
A baby should not have to work hard to breathe during a feed. The nose may touch the breast, but the nostrils should remain open. If breathing looks difficult, remove the baby gently and seek medical help.

How milk moves from the breast
Milk removal begins with stimulation. When the baby suckles, nerves in the nipple and areola send signals to the brain. The brain releases prolactin, which supports milk production, and oxytocin, which helps milk move through the ducts.
This movement is called the milk ejection reflex, or let-down. Some parents feel tingling or pressure. Others feel nothing at all. Lack of a noticeable sensation does not mean milk is not flowing.
Newborn breastfeeding mechanics work best when the baby removes milk often and effectively. Frequent milk removal tells the body that more milk is needed. Long gaps, poor latch, or limited milk transfer can reduce this signal over time.
Milk flow changes during a feed. Early milk may flow more quickly. Later milk is often richer in fat, although breast milk does not switch from one type to another at a precise moment. The breast gradually changes as it empties.
A parent’s stress level can affect oxytocin release for some people. This does not mean stress makes breastfeeding impossible. Calm breathing, skin-to-skin contact, warmth, privacy, and support may help the reflex work more easily.

Signs that milk transfer is working
Milk transfer means the baby is moving milk from the breast into the mouth and swallowing it. A baby can appear to suck often without taking in much milk, so several signs matter.
Look for these positive signs:
• The baby begins with quick sucks, then uses deeper rhythmic sucks.
• Swallows become regular during active feeding.
• The cheeks stay rounded rather than dimpling inward.
• The breast feels softer after the feed.
• The baby releases the breast or appears relaxed.
• Urine output rises during the first several days.
• Weight begins to increase after the normal early loss.
In the first days, wet diapers usually increase day by day. Many newborns have at least one wet diaper on day one, two on day two, and so on, though individual patterns vary. By about day five, many healthy breastfed newborns have at least six wet diapers each day.
Stool patterns also change. Early stools are dark and sticky. They usually become lighter and looser over the next few days. Your pediatric clinician should assess feeding if the baby has very few wet diapers, remains unusually sleepy, or does not begin gaining weight.
Weight checks are one of the best ways to assess newborn breastfeeding mechanics. Diaper counts help, but they cannot replace a clinical exam or a measured feeding when needed.

Positions that support effective breastfeeding
There is no single best breastfeeding position. The best position keeps the baby close, the head and body aligned, and the parent comfortable.
Cradle hold
The baby rests across the front of the body. This position can work well once the baby latches easily and the parent feels confident guiding the head.
Cross-cradle hold
The opposite arm supports the baby’s neck and shoulders. This gives more control during the early days and can help with latch practice.
Football hold
The baby rests beside the parent, with the feet pointing toward the back. This may help after a cesarean birth or with twins.
Side-lying position
The parent and baby lie on their sides. This can support rest, but the parent should move the baby to a separate safe sleep surface after feeding. Never feed on a couch or soft chair if you may fall asleep.
Laid-back position
The parent reclines, and the baby lies tummy-down on the chest. Gravity helps keep the baby close. Many babies use natural reflexes to move toward the breast in this position.
No matter the hold, keep these points in mind:
• Baby’s ear, shoulder, and hip should stay in one line.
• The chest should face the parent’s chest.
• The head should not be forced into the breast.
• The baby’s neck should remain slightly extended.
• Pillows should support the parent’s arms, not push the baby away.
Good positioning supports good newborn breastfeeding mechanics. It reduces strain and gives the tongue and jaw a better path for milk removal.
What painful breastfeeding may mean
Some tenderness during the first few seconds can occur as the body adjusts. Ongoing pain, cracked nipples, bleeding, or a pinching feeling usually needs attention.
Possible causes include:
• A shallow latch.
• The baby’s body turned away from the breast.
• The nipple entering the mouth at the wrong angle.
• Strong suction without enough breast tissue in the mouth.
• Nipple damage from pulling the baby off without breaking suction.
• Breast inflammation or infection.
To release suction, place a clean finger gently into the corner of the baby’s mouth. Then try again. Do not pull the baby straight off the breast.
If the nipple looks flattened, creased, or white after feeding, the latch may be too shallow. A lactation professional can watch a full feed and suggest a small adjustment. Hands-on assessment is often more useful than trying many new positions alone.
Get prompt medical advice for fever, a hot red area on the breast, severe pain, pus, or symptoms that worsen quickly. These may signal mastitis or another condition that needs care.
Newborn breastfeeding mechanics and pumping
A breast pump does not copy every part of a baby’s mouth. A pump uses repeated suction, while a baby uses suction, tongue movement, jaw compression, and breast shaping.
A pump can still remove milk well when the flange fits and the settings are comfortable. Painful suction is not better suction. Start with a low setting, increase slowly, and stop if the nipple rubs or swells.
When pumping:
• Center the nipple in the flange.
• Check that the nipple moves freely.
• Use the lowest comfortable suction.
• Massage or compress the breast gently if milk flow slows.
• Wash pump parts as directed.
• Store milk using current guidance from public health agencies.
If a baby cannot latch, expressed milk can help maintain nutrition while the feeding problem is assessed. A newborn with poor transfer may need a temporary feeding plan that includes nursing, pumping, and supplemental milk. This plan should be individualized by a pediatric clinician or lactation professional.

Common challenges that affect milk transfer
Newborn breastfeeding mechanics may change from feed to feed. Babies are not machines, and hunger, sleep, illness, and milk flow all affect performance.
Sleepy newborn
A sleepy baby may need skin-to-skin contact, a diaper change, or gentle stimulation before feeding. If the baby rarely wakes to feed, cannot stay attached, or has too few wet diapers, contact the pediatric care team.
Fast milk flow
A strong let-down may cause gulping, coughing, or pulling away. Reclining while feeding can slow the flow. Burp the baby and offer the breast again when the baby is calm.
Slow milk flow
Breast compression may help during active sucking. Switching sides after the baby stops swallowing can also help, but frequent switching without watching milk transfer may reduce the amount taken from each breast.
Premature birth
Premature babies may tire quickly and have less mature suck-swallow-breathe coordination. They may need paced feeds, expressed milk, or close weight monitoring.
Engorgement
A very firm breast can make it hard for a baby to latch. Hand express a small amount first to soften the areola. Avoid aggressive massage, which may increase swelling.
Bottle flow preference
Some babies become frustrated when a bottle flows faster than the breast. Paced bottle feeding, with the bottle held more level and frequent pauses, can support a slower rhythm.
The goal is not perfect feeding at every session. The goal is safe, comfortable, effective milk transfer over time.
When to seek professional help
Early support can prevent a small latch issue from becoming a larger supply or weight problem. Ask for help if feeding remains painful or if you feel unsure about what you see.
Contact a health professional if:
• The baby feeds fewer than eight times in 24 hours during the early weeks.
• The baby cannot latch or repeatedly slips off.
• You do not see or hear regular swallowing.
• The baby has fewer wet diapers than expected.
• The baby remains very sleepy or difficult to wake.
• The baby looks yellow and is feeding poorly.
• Weight loss is greater than expected or weight gain is slow.
• Your nipples are cracked, bleeding, or severely painful.
• The baby coughs, chokes, or struggles to breathe often.
A pediatric clinician can check hydration, jaundice, oral anatomy, and weight. A lactation consultant can observe latch, positioning, and milk transfer. In the United States, an International Board Certified Lactation Consultant is trained to provide advanced lactation support, but other skilled professionals may also help.
Newborn breastfeeding mechanics cannot be judged from one detail alone. A tongue’s appearance, a feeding length, or a single wet diaper does not tell the whole story.
Frequently Asked Questions About Newborn Breastfeeding Mechanics
How should a newborn suck during breastfeeding?
A newborn often starts with quick, light sucks to trigger milk release. The pattern usually changes to deeper, slower sucks with pauses and swallows as milk flows.
Should breastfeeding hurt when the baby latches?
Brief tenderness may occur, but sharp, pinching, or lasting pain is not a goal. Pain often points to a shallow latch or positioning issue and should be assessed if it continues.
How can I tell if my newborn is swallowing milk?
Look for a brief pause after sucking, a deeper jaw movement, or a soft swallowing sound. The baby may also relax the hands and body during effective milk transfer.
Why does my newborn keep falling asleep at the breast?
Newborns may become sleepy because feeding is tiring, milk flow slows, or they are not transferring milk well. Try skin-to-skin contact and gentle stimulation, and seek care if the baby is hard to wake or has poor diaper output.
Can a tongue-tie affect newborn breastfeeding mechanics?
It can affect tongue movement in some babies, but not every baby with a visible frenulum has a feeding problem. Assessment should focus on pain, latch, milk transfer, and weight gain rather than appearance alone.
How often should a newborn breastfeed?
Many newborns feed at least eight to twelve times in 24 hours, though patterns vary. Feed based on early hunger cues and follow the baby’s weight, diaper output, and clinical advice.
What does a good breastfeeding latch look like?
The baby’s mouth should be wide, the lips should turn outward, and the chin should touch the breast. Sucking should feel like steady pulling, not repeated pinching.
Can I improve breastfeeding mechanics with a breast pump?
A pump can support milk removal, but it does not use the same tongue and jaw actions as a baby. Correct flange size, comfortable suction, and professional guidance can improve pumping results.
Conclusion
Newborn breastfeeding mechanics depend on a deep latch, a working tongue, steady jaw movement, and safe suck-swallow-breathe coordination. Good positioning helps these actions work as a team, while regular milk removal supports milk production.
Watch the whole picture: comfort, swallowing, diaper output, breast softness, and weight gain. If feeding hurts or the baby seems too sleepy, ask for help early rather than waiting for the problem to grow. Use this guide as a starting point, discuss concerns with your pediatric care team, and explore trusted lactation resources for hands-on support.


